
Dental Medical Billing Services
Dental Medical Billing Services for Your Practice
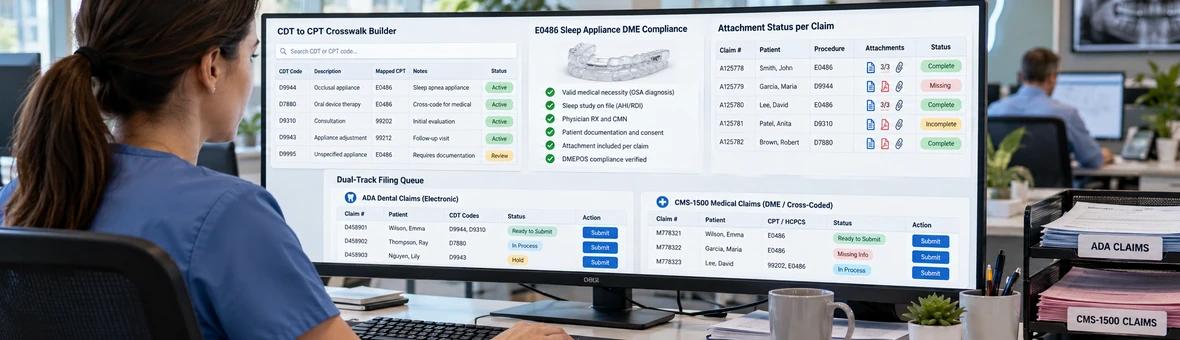
Medbilling RCM runs dental billing on two tracks. Routine claims ship on ADA forms with CDT codes. Procedures that qualify for medical reimbursement get cross-coded to CPT on CMS-1500 through the medical clearinghouse. Sleep appliances and TMJ splints are the most common crossover cases. If your practice doesn't have cross-coding volume, a dental-only billing company is a better fit.

Where the revenue goes missing
Revenue your practice earned but never collected
Dental plan maximums haven’t moved in decades, but procedures that qualify for major medical reimburse on a separate benefit pool with no annual cap. Most practices never cross-code those claims. The rest of the revenue leaks are operational: missing attachments, wrong payer sequence, denials with no follow-up. That is what a dental medical billing team runs down.
Five-Phase Operating System
How the Revenue Control Framework runs for dental practices
Five phases run from verification through payment posting. Each one closes a specific revenue gap.
We verify dental PPO and medical benefits on the same patient. Our medical credentialing team handles pre-authorizations and payer enrollment for qualifying cases.
Dental Cross-Coding Reference
Procedures we cross-code to medical every week
Verified against AMA CPT 2026, ADA CDT 2026, and NCCI bundling edits.
TMJ occlusal splint
ICD-10 M26.62, M26.69
Document joint dysfunction, not just bruxism
CBCT maxillofacial
ICD-10 M27.2, M26.60
Medical necessity for pathology or TMJ only
Bone graft
ICD-10 M27.0, M27.8
Reconstructive only, not socket preservation
Clinical stays with your team. Billing moves to ours.
PMS and Clearinghouse Compatibility
Works with your dental software. No revenue gap when you switch.
Your PMS stays in place. Claims in progress stay in progress. We work open AR instead of writing it off. DSO groups get consolidated reporting across locations. We handle multi-location billing when sites operate under separate entities. BAA signed before we touch anything.
Get a Free Revenue Assessment
Common Questions
What dental practices ask before switching
Q01What documentation do you need for E0486 sleep appliance billing?
A diagnostic sleep study (AHI 15+ or 5+ with comorbidities), documented CPAP intolerance, a Standard Written Order, a PDAC-verified appliance, and a signed Proof of Delivery. Claims ship with Modifier KX and NU.
Q02How do you handle claim attachments?
X-rays, perio charts, and narratives go out with the claim on first filing. No follow-up requests from the payer for missing documentation.
Q03Can you bill both dental and medical on the same patient?
Yes. Medical primary on qualifying procedures. EOB routes to dental secondary. Higher reimbursement gets captured first. Dental benefits stay available for routine care.
Q04Do you work inside our dental software?
Yes. Our team works directly inside your PMS via secure remote access. We post payments, adjust write-offs, and generate secondary claims. Our physician billing team handles the medical claim track.
Q05What does onboarding look like?
You provide PMS access, your PPO fee schedules, and your attachment workflow. We handle the rest. Most practices are fully transitioned within five business days.
Q06How is pricing structured?
Percentage of net collections. No setup fees, no monthly minimums, no long-term contracts.
Ready when you are
Your revenue assessment is built from your own claims data
We'll pull a sample of your claims and show you your attachment compliance rate, cross-coding revenue gap, denial rate by CDT code, and aged AR by payer. That assessment is how our dental billing services start for every practice.
- Attachment compliance rate
- Cross-coding revenue gap
- Denial rate by CDT code
- Aged AR by payer